IBD Skin Symptoms: Are They Caused by Inflammation or Medication?

Written by: Nasim Moussavi Harami, PharmD, RPh
Updated: November 2nd, 2026
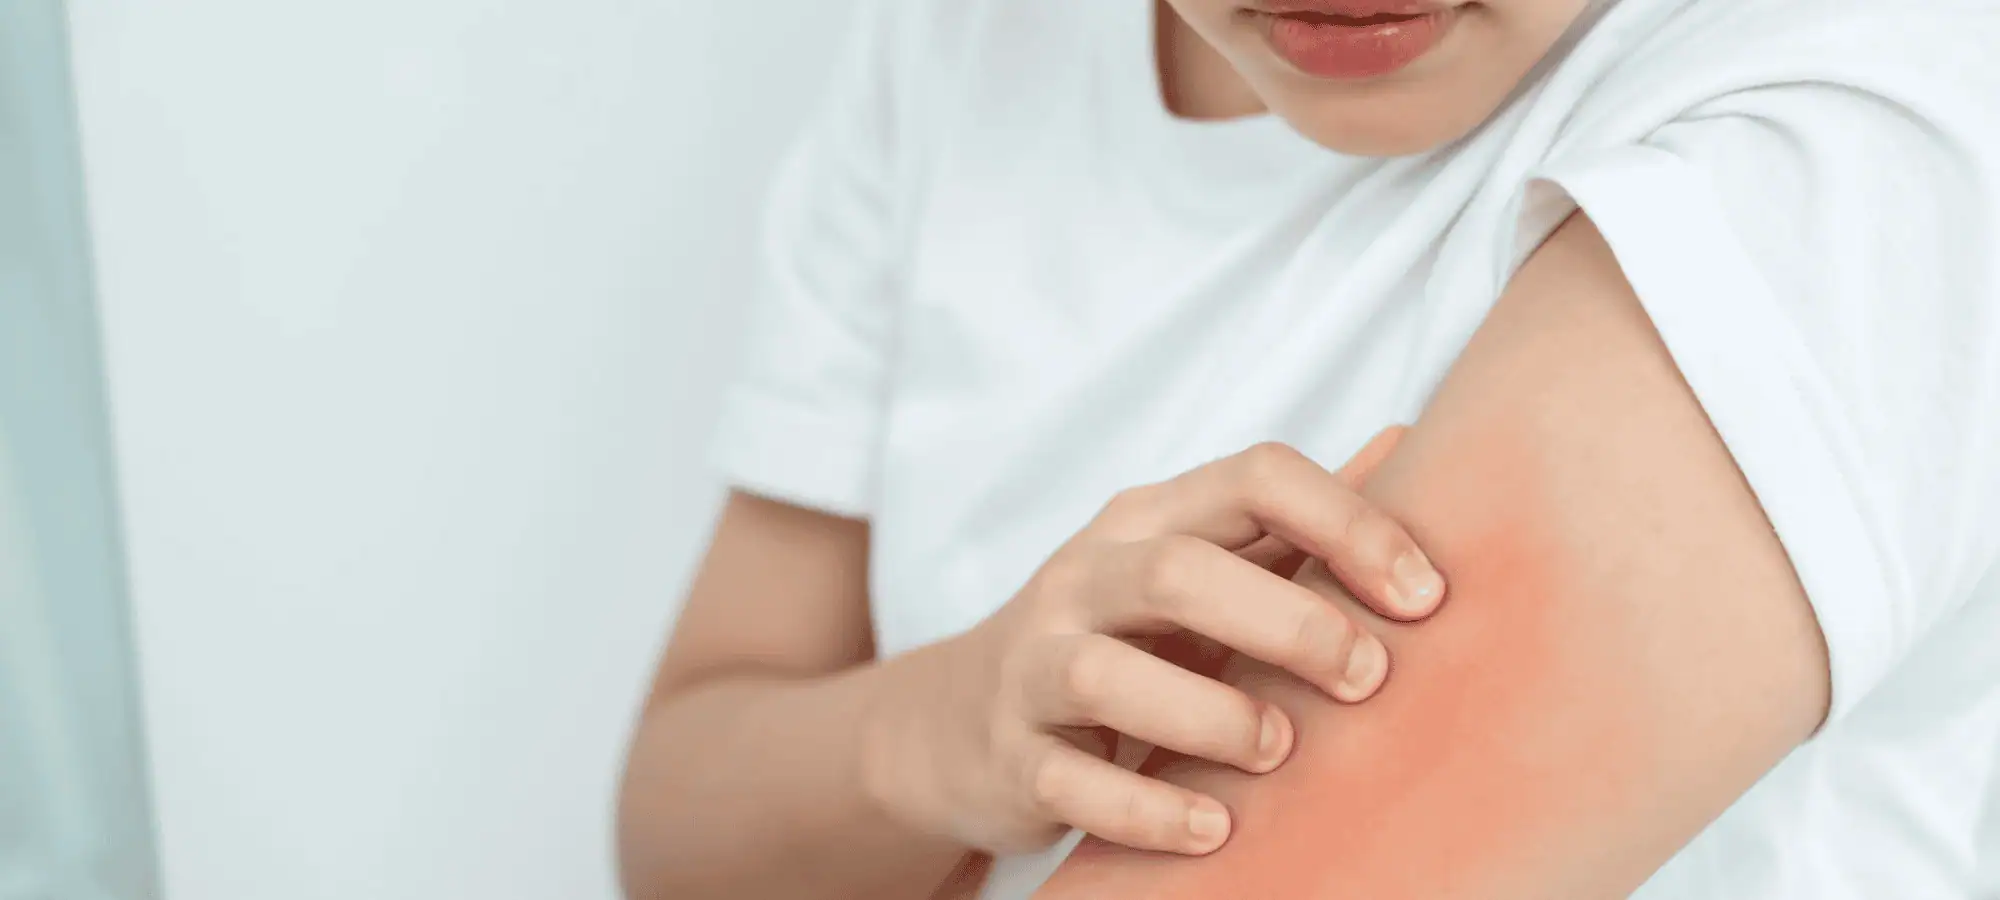
If you live with Crohn’s disease or ulcerative colitis, you already know IBD doesn’t always stay in the gut. A new rash, tender bump, mouth sore, or painful skin change can show up alongside digestive symptoms – or even when your IBD otherwise seems quiet.
The confusing part is figuring out why. An IBD skin symptom might come from the inflammation behind IBD itself, a separate immune-related condition, a nutrient shortfall, or a medication. Sometimes the skin problem has nothing to do with IBD at all. The timing and pattern often offer the best clues, so this article walks through the most common IBD skin symptoms, how treatment can help (and sometimes complicate things), and what to do when something new appears.
Why Can IBD Affect the Skin?
Crohn’s disease and ulcerative colitis are immune-mediated conditions. Although the inflammation centres in the digestive tract, that same immune activity can affect other parts of the body, including the skin.
The exact gut-skin connection is still being worked out. Research points to several possible links, including shared immune pathways, genetics, and changes in gut bacteria – mechanisms that likely overlap rather than act alone.
Skin involvement isn’t rare, either. ECCO guidelines estimate that cutaneous manifestations occur in about 15% to 20% of people with IBD, and research suggests these changes can sometimes appear before any digestive symptoms show up at all.
Nutrition can be part of the picture too. Active inflammation, reduced food intake, and malabsorption can all raise the risk of nutrient shortfalls. Guidelines recommend checking for deficiencies when clinically appropriate, since low iron, zinc, or vitamin B12 can affect the mouth, skin, hair, or nails.
What Skin Conditions Are Linked to IBD?
Two conditions come up most often in current clinical guidelines: erythema nodosum and pyoderma gangrenosum.
Erythema nodosum appears as tender, raised bumps, most often on the shins or lower legs, and can look red, reddish-purple, or darker than the surrounding skin. It often tracks with intestinal inflammation, so it may appear during a flare and improve as the underlying IBD comes under better control. Both the 2023 cutaneous review and ECCO guidance describe this close relationship with disease activity. That said, infections and medications can cause it too, so a new episode still deserves a proper look.
Pyoderma gangrenosum is rarer but more serious. It typically starts as a small bump or pustule and develops into a deeper, painful open sore, often with an irregular, darker border, most commonly on the legs or around a stoma – a surgically created opening in the abdomen used to pass stool. Unlike erythema nodosum, it doesn’t reliably rise and fall with digestive activity. One especially important feature is pathergy – when relatively minor skin trauma, such as a cut, scrape, or even an injection, can trigger a new lesion or make an existing one worse.
A 2026 multicenter study found that coordinated dermatology and gastroenterology care gives the best results, with the skin often improving alongside the underlying IBD.
A few other associated conditions round out the picture:
- Psoriasis – scaly, itchy patches on the scalp, elbows, knees, or skin folds; more common in people with IBD than in the general population but doesn’t usually track with a flare the way erythema nodosum does.
- Hidradenitis suppurativa – recurring painful lumps or draining areas in skin folds like the armpits or groin, more frequent in Crohn’s disease and linked to IBD in both directions.
- Mouth sores (aphthous stomatitis) – painful round ulcers inside the lips or cheeks that a 2024 review describes as more noticeable when IBD is active, though nutrient shortfalls and infection can cause them too
How Can Medications Help IBD-Related Skin Symptoms?
Sometimes the most effective way to improve a skin problem is treating the IBD itself. Erythema nodosum is a good example – when it’s tied to active inflammation, it often improves as a flare settles.
Other conditions need care of their own. Pyoderma gangrenosum, for instance, is often managed jointly by gastroenterology and dermatology teams, sometimes using medications that calm the immune system directly.
What are biologics and where do they fit in for IBD?
Biologics are medications that target one specific part of the immune system responsible for driving inflammation, rather than affecting the whole body broadly. Think of them as more precise than older treatments – instead of suppressing immune activity everywhere, they block one particular signal that’s causing the problem.
Because some of those same signals drive both gut and skin inflammation, a biologic chosen to treat IBD can sometimes improve skin symptoms too. No single biologic works best for everyone, though – the right choice depends on how severe your IBD is, which skin condition you have, and what you’ve already tried.
What about biosimilars?
A biosimilar is a highly similar version of an existing biologic – somewhat like how a generic relates to a brand-name drug, though the comparison isn’t exact, since biologics are grown from living cells rather than manufactured chemically.
Before a biosimilar can be sold in Canada, Health Canada requires proof that it works the same way and is just as safe as the original biologic it’s based on – and that holds true even when someone switches from the original reference product to the biosimilar.
So, if a new skin symptom appears after starting or switching to a biosimilar, the timing is worth documenting and discussing with the IBD team – just as it would be with any biologic. However, the fact that a medicine is a biosimilar does not, by itself, mean that a different skin-side-effect profile should be expected..
Can IBD Treatment Itself Cause Skin Reactions?
Not every skin change during treatment comes from the disease. Some come from the medication itself – particularly a class of biologics called TNF inhibitors, which work by blocking one of the body’s inflammatory signals. A 2026 clinical review describes several patterns, including:
- Redness, swelling, or itching at an injection or infusion site
- Flushing, hives, or a rash during or after an infusion
- General rashes or eczema- like patches
- Infections, since some treatments affect immune function
- New or worsening psoriasis-like lesions, even without a personal history of psoriasis
That last one might sound backwards, since some of these same medications treat psoriasis in other contexts. Yet a 2022 meta-analysis of over 24,500 people with IBD on anti-TNF therapy found that around 6% developed this kind of reaction, known as “paradoxical psoriasis,” where the same treatment triggers a psoriasis-like flare instead.
A new rash doesn’t automatically mean treatment needs to stop. Depending on severity, skin-directed treatment alone may be enough. More persistent reactions may lead the care team to consider a change, ideally with dermatologist involved when the diagnosis is unclear.
What Should You Do About New or Changing Skin Symptoms?
The look of a rash alone often can’t tell you whether it’s inflammation, medication, or something unrelated – timing and pattern matter just as much. When something new appears, it helps to note:
- When it started, and whether you’d recently started, switched, or changed the dose of a treatment
- Whether it appeared after an injection or infusion
- Whether digestive symptoms were also flaring at the same time
- Where it started and how it’s behaving – spreading, painful, itchy, blistering, or draining
Photos are especially useful, since a rash can look different by the time of an appointment. Clear, well-lit photos – a close-up plus a wider shot showing where it is on the body – give your care team the most to work with.
Contact your IBD care team for anything persistent, painful, or hard to explain. A dermatologist may be especially helpful for a rapidly changing ulcer, recurring draining lumps, or psoriasis-like changes that are difficult to control.
One thing worth repeating: don’t stop or change an IBD medication on your own because of a new skin symptom. Some reactions can be managed while treatment continues; others may need a change. Either way, let the prescribing team assess it first.
IBD & Skin Symptoms – Reels with Nasim Moussavi
How IBD Affects Your Skin (Part 1)
Can IBD Treatments Affect Your Skin? (Part 2)
New Rash With IBD? What to know (Part 3)
When Is Urgent Care Needed?
Most rashes aren’t emergencies, but a few signs call for faster attention. Seek medical care for a rash that spreads rapidly, blisters or turns into open sores, comes with fever, is very painful, or involves the eyes, lips, mouth, or genital skin.
Trouble breathing or swallowing, or swelling of the face, lips, or tongue, can signal a severe allergic reaction and needs emergency care right away.

Key Takeaways
- IBD skin symptoms can come from inflammation, another immune-related condition, a nutrient shortfall, medication, or something unrelated to IBD.
- Erythema nodosum often tracks with disease activity, while pyoderma gangrenosum, psoriasis, and hidradenitis suppurativa may follow their own course.
- Some people notice skin symptoms before they’re ever diagnosed with Crohn’s disease or ulcerative colitis.
- Biosimilars for IBD are expected to perform the same as their reference biologic, including for skin-related side effects.
- Rapidly spreading, blistering, or feverish rashes – or swelling of the face or throat – need urgent medical attention.
- New skin symptoms are worth documenting and discussing with your care team before any treatment change.
The Bottom Line
IBD skin symptoms can be frustrating because the same complaint – a rash, sore, or painful bump – can have very different causes. Looking at the timing, the pattern, and what’s happening with your Crohn’s disease or ulcerative colitis at the same time can help your care team work out whether inflammation, medication, or something else is behind it.
If something changes, take a photo, note when it started, and bring it to your IBD care team. In many cases, the skin problem and the IBD can be managed together, without an unplanned change to treatment.
FAQs
Does a new skin symptom mean my IBD is getting worse?
Not necessarily. Erythema nodosum often tracks with active IBD, but conditions like psoriasis, hidradenitis suppurativa, and some treatment-related reactions can appear even when digestive symptoms are stable.
Can biologics for IBD cause skin reactions?
Yes. Depending on the medication, reactions can include injection-site or infusion reactions, eczema-like changes, infections, and psoriasis-like symptoms. Type and likelihood vary by treatment.
Can biologics also improve skin symptoms?
They can. If the same inflammatory pathway drives both gut and skin symptoms, an immune-targeted treatment may help both – the right choice depends on the specific skin condition and your IBD.
Can a biosimilar cause different skin side effects than a reference biologic?
A different safety profile isn’t expected simply because a medicine is a biosimilar. Health Canada requires evidence of no clinically meaningful difference before authorizing one. Any new symptom after a switch is still worth documenting and discussing.
Can skin symptoms appear before IBD is diagnosed?
Yes. Skin and mouth changes sometimes appear before a formal diagnosis. That doesn’t mean every rash points to IBD, but unexplained or recurring changes alongside digestive symptoms are worth raising with a doctor.
This resource was made possible due to an unrestricted educational grant from Organon.

References
- Amatore, F., Colombel, J.-F., & Delaporte, E. (2024). Mucocutaneous manifestations of inflammatory bowel disease. Annales de Dermatologie et de Vénéréologie, 151(3), 103301. https://doi.org/10.1016/j.annder.2024.103301
- American Academy of Dermatology Association. (n.d.). How to take pictures of your skin for your dermatologist. https://www.aad.org/public/fad/digital-health/taking-pictures-skin
- American Academy of Dermatology Association. (n.d.). Rash 101 in adults: When to seek medical treatment. https://www.aad.org/public/everyday-care/itchy-skin/rash/rash-101
- Bischoff, S. C., Bager, P., Escher, J., et al. (2023). ESPEN guideline on Clinical Nutrition in inflammatory bowel disease. Clinical Nutrition, 42(3), 352–379. https://doi.org/10.1016/j.clnu.2022.12.004
- Food Allergy Canada. (n.d.). Reaction signs and symptoms. https://foodallergycanada.ca/food-allergy-basics/preventing-and-treating-allergic-reactions/reaction-signs-and-symptoms/
- Gordon, H., Burisch, J., Ellul, P., et al. (2024). ECCO guidelines on extraintestinal manifestations in inflammatory bowel disease. Journal of Crohn’s and Colitis, 18(1), 1–37. https://doi.org/10.1093/ecco-jcc/jjad108
- Guse, J., Blesl, A., Esters, P., et al. (2026). International collaborative experiences in managing pyoderma gangrenosum in patients with inflammatory bowel disease. Therapeutic Advances in Gastroenterology. https://doi.org/10.1177/17562848261461012
- He, R., Zhao, S., Cui, M., Chen, Y., Ma, J., Li, J., & Wang, X. (2023). Cutaneous manifestations of inflammatory bowel disease: Basic characteristics, therapy, and potential pathophysiological associations. Frontiers in Immunology, 14, 1234535. https://doi.org/10.3389/fimmu.2023.1234535
- Health Canada. (n.d.). Biosimilar biologic drugs in Canada: Fact sheet. Government of Canada. https://www.canada.ca/en/health-canada/services/drugs-health-products/biologics-radiopharmaceuticals-genetic-therapies/applications-submissions/guidance-documents/fact-sheet-biosimilars.html
- Schmieder, S. J., & Krishnamurthy, K. (2023). Pyoderma gangrenosum. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK482223/
- Tsilimpotis, D., Kyriakou, G., Biedermann, L., Vavricka, S. R., Greuter, T., Rogler, G., & Doulberis, M. (2026). Cutaneous manifestations and dermatologic adverse events in IBD: A clinical update. Inflammatory Bowel Diseases, 32(3), 542–561. https://doi.org/10.1093/ibd/izaf228
- Xie, W., Xiao, S., Huang, H., & Zhang, Z. (2022). Incidence of and risk factors for paradoxical psoriasis or psoriasiform lesions in inflammatory bowel disease patients receiving anti-TNF therapy: Systematic review with meta-analysis. Frontiers in Immunology, 13, 847160. https://doi.org/10.3389/fimmu.2022.847160










Infliximab for the Treatment of Inflammatory Bowel Disease: An Overview of Drug History and Delivery